
Gastric Sleeve Surgery in Northern Virginia
Laparoscopic sleeve gastrectomy — the most widely performed weight-loss operation
Accuracy of the medical content was verified by Dr. Matthew Fitzer, M.D., FACS, FASMBS, a board-certified bariatric surgeon. (He authored most of it.) Read Dr. Fitzer's professional bio
Gastric sleeve surgery is the most common weight loss surgery in the world. You may also hear it called laparoscopic sleeve gastrectomy, vertical sleeve gastrectomy (VSG), or simply "the sleeve."
How the sleeve works
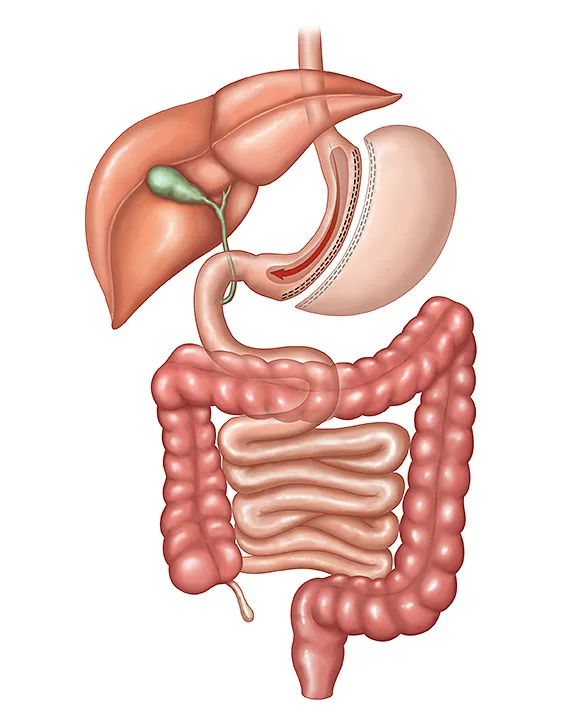
The operation removes about 80% of the stomach and leaves a slim, banana-shaped tube behind. That smaller stomach holds far less food, so it limits food intake. Used right, it gives you a strong sense of fullness after a surprisingly small amount of food.
It also works through hormonal changes. The part of the stomach we remove is the main source of ghrelin, a powerful hunger hormone. Together, the two effects create substantial, lasting weight loss and relief from obesity-related health problems.
~70% EWL
average excess weight loss in the first 1–2 years
~80%
of the stomach is removed to form the sleeve
#1
the most common weight-loss operation worldwide
Who is a candidate for sleeve gastrectomy?
We offer the sleeve to adults with a body mass index (BMI) of 35 or higher. A BMI of 30 or higher also qualifies if you have an obesity-related health condition. For patients of East Asian descent, those numbers drop to 32.5 and 27.5.
But your BMI is not the whole picture. We look at your medical history. We look at what you have already tried through diet and exercise. And we look at whether you are ready to change how you eat for good. See our full bariatric surgery requirements for BMI thresholds, comorbidity criteria, and age guidance.
The presence of acid reflux (GERD) may impact the decision whether to get a sleeve. The sleeve can trigger new acid reflux, and it often worsens existing reflux. If you already have bad reflux, a gastric bypass may suit you better. Bypass usually improves reflux. It rarely makes it worse. Dr. Fitzer will discuss this and other considerations with you.
What happens during sleeve surgery
Dr. Fitzer performs the sleeve laparoscopically, with the patient under general anesthesia. He uses what we call the minimally invasive approach, which avoids a long incision. Instead, he works through five small incisions using slender instruments. Small incisions mean faster recovery and fewer wound problems.
During surgery, the stomach is cut into two pieces. One piece is the narrow tube—the sleeve—which stays in. The other piece is the larger, sack like part of the stomach. That piece comes out (through a surprisingly small hole).
The small intestine is left alone. Because food still travels its normal path, your body absorbs nutrients nearly as well as it did before, and the risk of nutritional deficiency is lower than with operations that reroute the bowel.
One thing to understand: the sleeve is not reversible. If we take a part of the stomach out, there's no way to save it for later. The sleeve can, however, be converted to another operation if problems come up.
Most cases take 35 to 75 minutes. You can watch Dr. Fitzer perform a sleeve on our YouTube channel.
Weighing the sleeve against the bypass? See our side-by-side comparison of gastric bypass and sleeve gastrectomy.
How much weight will I lose after sleeve gastrectomy?
Long-term weight loss outcomes
Sleeve patients lose more weight than LAP-BAND patients, though somewhat less than gastric bypass patients. Among Virginia Bariatric patients, excess weight loss averages over 70% from year one through year nine. Below is a graph of average % excess weight loss of Dr. Fitzer's actual sleeve patients from year one through year nine following their surgery. It was automatically generated by the electronic health record provider (Baritrax360) for the practice. Identical data was submitted to the MBSAQIP registry.

Weight regain after sleeve gastrectomy
If you are already years out from a sleeve and the weight is creeping back, read our guide to managing weight regain after bariatric surgery, which covers the biology behind regain, GLP-1 medications after surgery, and revision options.
Training matters
The large national registries (e.g., the MBSAQIP), provide data about the average long-term weight loss with sleeve surgery in the United States. The national average is steady at 60%, although weight loss varies from practice to practice. The important factor seems to be the focus of the operating surgeon.
More than half the sleeve procedures done each year in the U.S. are performed by surgeons who lack formal fellowship training in weight loss surgery. Sleeves may be a small part of their overall case volume.
When sleeve surgery is performed without formal training, the stomach often gets an over-cautious trim, not a proper volume reduction. Below are a few examples of patients with excessively large sleeves who were referred to Dr. Fitzer for sleeve revision:


The other type of sleeve surgeon is the bariatric surgeon. Bariatric surgeons typically have one or more years of formal fellowship training under their belt, and their practices are devoted exclusively to bariatric medicine and surgery.
Dr. Fitzer is this kind. He completed a year-long bariatric surgery fellowship at the University of Missouri in 2005-2006. Since fellowship, nearly 100% of his annual caseload has been bariatric procedures.
Bariatric surgeons can be relied on to perform proper stomach reduction. Here are a few examples of imaging studies from Dr. Fitzer's own sleeve patients (identifying information removed):


When someone loses very little after a sleeve or regains most of the lost weight, the sleeve may be at fault. The good news is that an underperforming sleeve can usually be repaired without much difficulty. See Revisions.
Health benefits of sleeve gastrectomy beyond weight loss
Losing weight with the sleeve often improves obesity-related conditions, and in many cases clears them entirely. Type 2 diabetes, high blood pressure, high cholesterol, sleep apnea, and joint pain all tend to get better.
Blood sugar control often improves within days of surgery, long before you have lost much weight. Favorable changes in your gut hormones drive that early effect.
The sleeve also offers several practical advantages over more complex operations:
- It is a simpler operation than gastric bypass, with a shorter time under anesthesia.
- The hospital stay is usually a single night.
- Complication rates are low.
- Nutrient absorption stays close to normal, because the small intestine is untouched.
- Your stomach and intestine remain reachable by endoscope, which matters if you ever need one.
Recovery after the sleeve operation
Recovery timeline
The hospital stay is short. Most patients go home after one night and return to normal activities within four weeks.
Your diet advances in stages. You start clear liquids in the hospital, move to liquids and protein shakes at home for the first week, then spend a week on pureed and soft foods. After about eight weeks you are back to regular solid food, in much smaller portions than before surgery.
Daily vitamins begin the day you get home. The recommended vitamin supplements can be viewed or downloaded here. Over your first year you will see Dr. Fitzer and his dietitian regularly.
Many patients find the shift to smaller meals easier than they feared. Even so, one-on-one work with an experienced eating coach makes a real difference. Building new eating habits takes time and support, and our team provides both throughout.
Risks and side effects of sleeve gastrectomy
Sleeve gastrectomy has a strong safety record, and serious complications are rare. Most of the risks are the treatable problems that are occasionally seen after any kind of surgery: bleeding, infection, and blood clots.
A complication of great concern is a leak from the stomach staple line. Leaks are rare, thankfully. When they happen, it’s usually within the first few weeks. They are also treatable, but treatment should not be delayed.
Early side effects are usually mild and temporary. Nausea, fatigue, and soreness at the incisions typically settle within the first few weeks as your diet advances.
Long term complications are uncommon, except for one. Some 10 or 20% of patients get new or worse acid reflux.
Acid reflux and the sleeve
Why should sleeve surgery cause reflux? The pictures below help explain it.
Notice how the normal stomach contains more fluid, yet the waterline settled below the opening of the esophagus.
In the sleeved stomach, the fluid sits on top of the esophageal opening. While the patient lays that way, gravity will keep trying to pull the acidic juice back into the esophagus.
It’s normal for the esophagus to get some exposure to stomach acid. Reflux symptoms and esophageal damage only tend to develop when the daily duration of exposure rises above a threshold of 4-6%. The extra nighttime acid exposure after a sleeve pushes some patients over that symptom threshold.
Gastric sleeve surgery: frequently asked questions
Is any part of my stomach or intestine bypassed?
No. The sleeve removes part of your stomach, but it does not reroute your intestines. Food follows its normal path. That is one reason nutrient absorption holds up better than it does after a gastric bypass.
Sleeve or bypass — which is better?
Both are excellent operations, with similar weight loss and similar rates of diabetes remission. The sleeve is simpler and carries fewer complications. Bypass is often the better choice if you have significant acid reflux or certain metabolic conditions. The right answer is individual. See our detailed sleeve vs. bypass comparison for a side-by-side look.
Can the sleeve be reversed?
No. Part of your stomach is removed permanently, so the sleeve cannot be undone. It can, however, be converted to another operation later if you ever need that.
How long is recovery after gastric sleeve surgery?
Most patients stay one night in the hospital and return to normal activities within about four weeks. You start on a liquid diet right away, then move through pureed, soft, and regular foods over the next eight weeks.
Is gastric sleeve covered by insurance?
Many major insurers cover sleeve gastrectomy when you meet their medical criteria, usually a BMI of 40 or higher, or 35 or higher with an obesity-related condition. Our team verifies your benefits and walks you through authorization. Our insurance coverage guide has plan-specific detail on Anthem BCBS, Aetna, Medicare, and others. If you are covering the cost yourself, our self-pay page lists the price of sleeve gastrectomy and what is included.
What diet do I follow after sleeve gastrectomy?
Eating advances week by week for eight weeks: clear liquids, then full liquids and protein shakes, then pureed and soft foods, and finally regular solid food. Sleeve-specific diet instructions can be found here, Our dietitian is there to support you through every stage.
Next steps: schedule a gastric sleeve consultation
Considering the sleeve? The first step is a consultation. We review your health history and your goals, and we figure out together whether the sleeve is the right option for you.
Not using insurance? See how much a gastric sleeve costs self-pay: an estimated $19,200, which covers the surgeon fee, one hospital day at INOVA Fair Oaks Hospital, an anesthesia estimate, and a year of routine follow-up with Dr. Fitzer. You can also review our financing options.
Selected medical references
- Han Y, et al. Comparative analysis of weight loss and resolution of comorbidities between laparoscopic sleeve gastrectomy and Roux-en-Y gastric bypass: a systematic review and meta-analysis based on 18 studies. Int J Surg. 2020;76:101-110. doi:10.1016/j.ijsu.2020.02.035
- Guan B, et al. Mid-long-term Revisional Surgery After Sleeve Gastrectomy: a Systematic Review and Meta-analysis. Obes Surg. 2019;29:1965-1975. doi:10.1007/s11695-019-03842-3
Last updated: